Tag

skin of color dermatology

A Practical Guide to Managing CSU in Patients With Skin of Color

By Sessions

chronic spontaneous urticaria

At Skin of Color Update 2025, Mona Shahriari, MD, FAAD, provided a comprehensive overview of chronic spontaneous urticaria (CSU). CSU is a condition frequently managed by both dermatologists and allergists. Dr. Shahriari challenged dermatologists to embrace CSU as a condition that can be confidently managed without necessitating a referral.

CSU affects about 1% of the population, with a prevalence of 230 per 100,000 adults. It is most common in individuals 20–40 years old, and some data suggests a higher prevalence in Black populations in comparison to White populations. CSU is defined by the presence of itchy wheals (hives) and/or angioedema for at least six weeks, with individual hives lasting less than 24 hours and angioedema up to 72 hours. And by definition, there must be no identifiable trigger.

The disease is mast cell-mediated, with a rapid onset of symptoms when triggered. The pathogenesis of CSU can be likened to a piñata. When a mast cell is triggered, it’s as if the pinata is hit, and now all the proteins, like histamine, that are inside the mast cell, pour out, akin to candy pouring out of a pinata.

There are several comorbid conditions that can occur concomitantly with CSU with autoimmune thyroid disease being one of the most common. Interestingly, females with CSU have a 20-fold increased risk for rheumatoid arthritis and hypothyroidism at 10 years. Vitiligo, type 1 diabetes, pernicious anemia, and atopic diseases are other comorbidities that are commonly seen in patients with CSU.

CSU is an often misunderstood skin disease that disproportionately affects quality of life, especially in patients with skin of color, where diagnosis and management can be uniquely challenging. The clinical features of wheals and angioedema are consistent across skin types, but erythema is less visible in skin of color, making diagnosis more difficult. Videos may be more useful than photos for assessing lesion elevation in these patients.

The burden of CSU is substantial, with up to 40% of patients experiencing a very large negative impact on quality of life, including sleep disturbance, anxiety, and depression. Itch is the most burdensome symptom.

Diagnosis is clinical. International guidelines recommend a focused history, symptom assessment, and limited laboratory workup (CBC and ESR/CRP, with the option of anti-thyroid peroxidase IgG, and IgE levels when indicated). Extensive allergy testing and biopsy are not required unless atypical features are present. In those instances, the additional work up would be to rule out other conditions, not rule in CSU.

Diagnostic delays are common, with patients often symptomatic for 2–3 years before diagnosis, partly due to the intermittent nature of CSU. Patients are frequently referred to multiple clinicians and cycle through various antihistamines and corticosteroids before finally getting the correct diagnosis. The differential diagnosis is broad and includes urticarial vasculitis and bullous pemphigoid. The transient nature of CSU lesions (<24 hours) is a key distinguishing feature.

Management should be proactive and guideline-driven. The goal of treatment should be to control the disease, not cure it. Second-generation H1-antihistamines are first-line, with dose escalation if needed. If symptoms persist, omalizumab, dupilumab, and remibrutinib are appropriate second-line agents to consider. Dupilumab, which has been used by dermatologists to treat atopic dermatitis since 2017, is an appealing first-line option, since dermatologists are familiar with its dosing and safety. There are various other mediations that are being studied in the management of CSU. Dr. Shahriari dispelled existing safety concerns regarding the use of omalizumab, emphasizing that anaphylaxis is very rare and was only seen in the asthma trials, a population which is at higher risk at baseline, and was not seen in urticaria trials. Of note, data suggested that patients with skin of color are less likely to receive omalizumab, which clinicians need to be aware of to ensure equity in disease management.

In summary, recognizing the nuances of CSU in skin of color, especially the subtlety of erythema and the importance of video documentation, can improve diagnostic accuracy and patient outcomes. Dermatologists should avoid cycling through multiple antihistamines and have a low threshold to consider advanced targeted therapies for CSU, like dupilumab, remibrutinib and omalizumab. Prednisone should be avoided and only used as a short-term bridge in unique circumstances, not as monotherapy. With the latest developments in the CSU space and the approval of medications that we are dermatologists are quite familiar and comfortable with, dermatologists should feel empowered to take back ownership of this disease to optimize outcomes for patients.

This information was presented at the 2025 Skin of Color Update conference by Mona Shahriari, MD, FAAD. The above highlights from this lecture were written and compiled by Jay Nguyen, DO.
Vaccine- and Immunotherapy-Induced Vitiligo

By Posters

immunotherapy-induced vitiligo

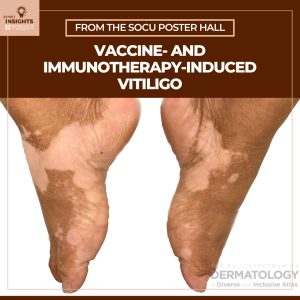
New-onset vitiligo may be a side effect of a preventative or therapeutic medical treatment, such as a vaccine or immunotherapy. When patients on immunotherapy experience vitiligo, it’s considered a positive prognostic indicator. Cancer vaccines, biologics, immune checkpoint inhibitors, and the COVID-19 vaccine can also induce vitiligo, though what this reveals about a person’s health is unknown. In patients with darker skin tones where vitiligo may be more apparent, the development of vitiligo can have unique psychosocial impacts.

A poster presented at Skin of Color Update 2025 investigates the pathogenesis of vaccine- and immunotherapy-induced vitiligo — including the impact of these conditions on patients with skin of color — and shares management strategies for dermatology clinicians. I interviewed the poster’s lead author, Sara Omari of the William Carey University College of Osteopathic Medicine.

You investigated the factors which contribute to the pathogenesis of vitiligo induced by immunotherapies and vaccines. How did you conduct your review and what did you discover?

We reviewed a variety of studies including clinical trials, case series, systematic reviews, and other studies on the topic of immune-mediated vitiligo. We found that immunotherapies enhance antigen presentation and Th1 immune responses, leading to CD8+ T-cell-mediated destruction of melanocytes.

How common is immunotherapy-induced vitiligo (IIV)?

IIV occurs in 2-16% of melanoma patients receiving immunotherapy, but the incidence varies by the particular agent examined.

IIV is a positive outcome for melanoma patients undergoing immunotherapy treatment. How is this the case?

The depigmentation effect reflects anti-melanocyte immunologic activity. Systematic reviews have shown that melanoma-associated vitiligo in particular is associated with lower disease progression and mortality. Hence, vitiligo-like depigmentation is a favorable prognostic marker in melanoma.

How long is the onset of IIV after immunotherapy treatment has started?

The onset of vitiligo will vary by immunotherapy. Vaccine-associated cases occur within 1-3 weeks, whereas biologics may induce vitiligo within one or more months after treatment.

You also looked at how IIV presents in patients with skin of color. Did you discover any research of the sort and, if so, what did you find?

In patients with darker skin tones, vitiligo is more visually apparent, more stigmatizing, and more likely to be misdiagnosed. Commonly cited misdiagnoses included tinea versicolor or post-inflammatory hypopigmentation.

How may dermatology clinicians do a better job of treating and researching IIV, especially in patients with skin of color?

Dermatologists and other providers should inquire about new-onset hypopigmentation in their patients, use a Wood’s lamp to rule out other causes, and address stigmatization and cultural norms. Further research is necessary to unveil the ways in which IIV uniquely affects patients with skin of color.

Is there anything else a dermatology clinician should know about vaccine- and immunotherapy-induced vitiligo?

Vitiligo in the setting of immunotherapy is not necessarily a sign of treatment failure. By contrast, it may be a positive prognostic indicator. Stigma reduction during treatment is especially important when treating patients with skin of color.

Additional authors of the poster include:

Sreshta Jannu, William Carey University of Osteopathic Medicine

Mashal Zaide, William Carey University of Osteopathic Medicine

Sumra Din, William Carey University of Osteopathic Medicine 

Radhika Misra, Rowan-Virtua School of Osteopathic Medicine

Daniel N. Thompson, William Carey University College of Osteopathic Medicine

Stuti Prajapati, St. John’s Episcopal Hospital

Addressing Comorbidities in Dermatologic Disorders: Spotlight on Psoriasis and HS

By Sessions

comorbidities in dermatologic disorders

At Skin of Color Update 2025, panelists, including Jennifer Soung, MD, FAAD, discussed how chronic inflammatory skin diseases, such as psoriasis (PsO) and hidradenitis suppurativa (HS), intersect with metabolic health, and highlighted emerging strategies for disease control, including the use of glucagon-like peptide-1 receptor agonists (GLP-1 RAs). This article summarizes key take-home points and clinical implications for dermatology practice.

The Link Between Weight, Inflammation & Skin Disease

Individuals with increased body mass index (BMI) are at a higher risk of developing psoriasis and are more likely to have severe disease. Obesity (as measured by increased BMI) is a chronic inflammatory state, with adipose tissue functioning as an active endocrine organ that releases cytokines and adipokines that amplify systemic and cutaneous inflammation.

In HS, systemic contributors including obesity, glucose intolerance, and hypertension may worsen disease severity. Panelists emphasized that treating “what we cannot see,” including metabolic disease, may be the foundational first step in successful HS management.

Comorbid obesity may also reduce response to biologic therapy. Many treatments for both psoriasis and HS are weight-based, which means that patients with higher BMI may have lower circulating drug levels, potentially affecting treatment outcomes. Despite this association, many patients do not recognize a relationship between their weight and its impact on their skin disease, emphasizing the need for further patient education.

GLP-1 Receptor Agonists: Weight Loss and Potential Skin Benefits

GLP-1 RAs, such as semaglutide and liraglutide, have transformed metabolic disease management by helping patients achieve meaningful weight reduction, often more than 10% of baseline body weight, which was previously not possible. These treatments can improve diabetes, hypertension, and other systemic health concerns closely linked to psoriatic disease.

Beyond metabolic improvement, emerging data suggests GLP-1 RAs may have anti-inflammatory benefits. GLP-1 receptors are distributed throughout the body, including on regulatory immune cells involved in psoriatic and HS disease pathways. Early clinical evidence suggests potential benefits of GLP-1 RAs in HS. Small real-world studies have reported decreased flare frequency, reduced pain, and improved quality of life when GLP-1 RAs were added to ongoing HS therapy. Although findings are preliminary, GLP-1 RAs may serve as a valuable adjunctive option in select HS patients, particularly those with a higher BMI. Ongoing studies are evaluating whether adding GLP-1 RAs to systemic therapy may enhance skin clearance and sustain response.

Communicating With Patients: Sensitivity & Shared Decision-Making

Discussing weight is highly sensitive due to cultural stigma and emotional impact. The panelists drew on their own personal experiences and recommended a permission-based, empathetic communication style. Asking first, “Would it be okay if we discuss how weight may affect your health and your skin?”, helps patients feel supported rather than judged.

Using language like “weight management” rather than “obesity” may improve engagement. Dermatologists are often the main physician a patient sees regularly, making it essential to encourage multidisciplinary support when appropriate.

Practical Recommendations for Dermatology Practice

Focus Area Recommendation
Baseline evaluation Record BMI and screen for metabolic comorbidities (hemoglobin A1c, lipids, blood pressure)
Care coordination Partner with primary care and obesity medicine when available
Therapy integration Consider addressing weight and systemic inflammation alongside skin-directed therapy
Patient language Use permission-based, stigma-free communication
Ongoing monitoring Track changes in BMI, metabolic control, skin activity, and quality of life

Take Home Points: 

Addressing underlying metabolic health is an integral part of treating inflammatory skin disease. Weight loss strategies and GLP-1 RAs represent a growing opportunity for dermatologists to improve outcomes in psoriasis and HS by reducing systemic inflammatory burden. While further research, particularly randomized controlled studies, is needed to define dermatologic benefits, early data and clinical experience suggest a promising multidisciplinary approach that supports both skin improvement and overall patient wellness.

This summary was prepared by Dr. Courtney Hanna, dermatology resident, who attended the session. The content reflects the resident’s notes and interpretations, may contain errors, and is provided for educational purposes only. It does not constitute official faculty endorsement and should not replace original sources or clinical judgment.

References:

American Journal of Managed Care. (2025). GLP-1s support weight loss, symptom relief in psoriasis, hidradenitis suppurativa. Retrieved February 2025, from https://www.ajmc.com/view/glp-1s-support-weight-loss-symptom-relief-in-psoriasis-hidradenitis-suppurativa

Gisondi, P., Del Giglio, M., Di Francesco, V., et al. (2008). Weight loss improves the response of obese patients with moderate-to-severe chronic plaque psoriasis to low-dose cyclosporine therapy. American Journal of Clinical Nutrition, 88(5), 1242–1247.

Jensen, P., Zachariae, C., Christensen, R., et al. (2013). Effect of weight loss on the severity of psoriasis: A randomized clinical trial. JAMA Dermatology, 149(7), 795–801.

Krajewski, P. K., Matusiak, Ł., & Szepietowski, J. C. (2024). The therapeutic potential of GLP-1 receptor agonists in hidradenitis suppurativa and other skin diseases. Journal of Clinical Medicine, 13(21), 6292.

Upala, S., Sanguankeo, A. (2015). Effect of lifestyle weight loss intervention on disease severity in patients with psoriasis: A systematic review and meta-analysis. Dermatology, 231(1), 70–74.

Xu, Y., et al. (2025). Association of BMI, BMR, BSA, and body weight with psoriasis treatment response. Translational Medicine Communications, 10(1), 30–45.


Navigating the Challenges of Pediatric Hidradenitis Suppurativa

By Uncategorized

pediatric hidradenitis suppurativa

Managing hidradenitis suppurativa (HS) presents unique clinical nuances, especially when caring for pediatric patients and communities of color where HS disproportionately carries a high burden of morbidity and psychosocial impact.

While up to one-third of all HS patients experience symptom onset before age 18, managing younger patients remains a complex balancing act. Because long-term safety data for systemic therapies in children is limited, dermatologists often must rely on off-label extrapolations from adult literature.

A poster presented at Skin of Color Update shares:

  • Presentation differences in children – and why early treatment matters
  • First-line options for therapeutics, and when to consider hormonal and biologic therapies
  • Safety considerations when prescribing systemics, including developmental risks and dosing dilemmas

Read the full interview with the poster’s lead author, Rachel Aronov of the Donald and Barbara Zucker School of Medicine at Hofstra/Northwell.

How to Prevent and Manage Laser & Device Complications in Patients With Skin of Color

By Sessions

laser and device complications

Patients with skin of color are at a greater risk of complications when treated with lasers and devices. Next Steps in Derm, in partnership with Skin of Color Update, interviewed Dr. Arielle Kauvar, clinical professor of dermatology at the NYU Grossman School of Medicine, for her pearls on preventing and managing complications. Watch as Dr. Kauvar explains the different cooling methods used to prevent pigmentary alterations due to laser and device treatment. Find out how Dr. Kauvar conducts pre-procedure exams and why she says they are important. Plus hear how taking certain steps before treatment can prevent complications.

Further Reading

If you want to read more about using lasers and devices in patients with skin of color, check out the following articles published in the Journal of Drugs in Dermatology:

A Single-Center, Open-Label, Prospective Study of a 589/1319 nm Dual Wavelength Laser for the Treatment of Facial Hyperpigmentation

ABSTRACT

Background: Facial hyperpigmentation, characterized by the excessive production of melanin in the skin, is a prevalent dermatological concern affecting individuals of various ethnic backgrounds.

Aims: To evaluate the safety and efficacy of a multi-wavelength 589/1319 nm dual-pulse duration laser device for the treatment of hyperpigmentation

Patients/Methods: A total of 17 healthy women (mean [SD] age of 43.4 [11.6] with skin phototype II-IV) were enrolled in this prospective, single-center study. Eligible participants received up to 3 treatments spaced 3 to 5 weeks apart with 2 follow-up visits at 4 and 12 weeks after the final treatment. Assessments included investigator ratings of skin quality, global aesthetic improvement, and hyperpigmentation. Safety and tolerability were monitored throughout the study.

Results: Significant improvements in hyperpigmentation and skin quality were observed at the 2 follow-up visits from baseline in most patients per investigator assessments. Patient satisfaction was high, and treatments were safe with transient self-resolving side effects such as erythema.

Conclusions: Laser treatments using a dual-wavelength 589/1319nm device significantly improve facial hyperpigmentation in patients of various skin types.

Supplement Individual Article: Algorithm for Pre-/Post-Procedure Measures in Racial/Ethnic Populations Treated With Facial Lasers, Nonenergy Devices, or Injectables

ABSTRACT

Background: Cosmetic procedures with lasers, nonenergy devices, and injectables are increasing in popularity among patients with skin of color. Published algorithms address measures to reduce side effects related to aesthetic procedures; however, none focus on reducing adverse events in skin of color.

Methods: An expert panel of dermatologists and plastic surgeons conducted face-to-face and online meetings to develop an algorithm for measures before, during, and after using aesthetic devices (energy and nonenergy-based) and injectable treatments based on the best available evidence for skin of color. Published algorithms and literature searches for aesthetic procedures provided guidance for the current algorithm. A modified Delphi method was used to reach a consensus to apply outcomes of literature searches, along with expert opinion, resulting in the current algorithm.

Results: The four sections of the algorithm outline an approach to optimize outcomes with specific before, during, and after procedure considerations. Pre-procedural consultation includes the development of a specific treatment plan based on individual patient goals and risk profile (including history and signs that may predict a higher risk for pigmentary or scarring complications). Before the procedure, sun avoidance and sunscreen use are emphasized; herpes simplex virus 1 prophylaxis and bleaching agents are administered if indicated. During the procedure, skin cleansing products are addressed, along with judicious techniques to minimize unintended cutaneous injury or inflammation. Post-procedural sunscreen and gentle skincare that may include skin-lightening agents or formulations designed to prevent infection and promote optimum healing are advised.

Conclusions: The algorithm strives to optimize treatment outcomes for patients with skin of color by providing their physicians with guidance on measures before, during, and after office-based medical aesthetic procedures.

Did you enjoy this video interview? Find more here.

Pigmentary Impact of Acne: SOCU Video Interview

By Sessions

pigmentary impact of acne

“Our patients hate these marks. They hate them more than they hated their acne to begin with.”  — Hilary Baldwin, MD, FAAD

Don’t miss this insightful interview on the pigmentary impact of acne, conducted by Next Steps in Derm in partnership with Skin of Color Update. Dr. Baldwin reviews how her management of acne and post‑inflammatory pigmentary changes has evolved. She shares practical, clinic-ready guidance including:

  • Whether to take an acne‑first approach or treat acne and hyperpigmentation simultaneously
  • Why “scars” is often the wrong term for certain post‑acne pigmentary changes
  • How she safely incorporates new over‑the‑counter topicals into patients’ routines to address pigmentary alteration

If you treat acne in patients with skin of color (or anyone troubled by persistent pigmentation), join us in Chicago June 6 and 7 for the Pigmentary Disorders Exchange Symposium. Sessions will address the pigmentary sequelae of inflammatory skin conditions, including acne and atopic dermatitis, as well as the latest in the management of pigmentary conditions, including melasma and vitiligo.

Scarring Alopecias: SOCU Interview with Dr. Susan Taylor

By Medical Dermatology

scarring alopecias

Scarring alopecias require early, effective treatment to stop progression and prevent further permanent hair loss. In an interview with Next Steps in Derm, in partnership with Skin of Color Update, Susan C. Taylor, MD, FAAD, shares the latest research in the understanding of scarring alopecias and how that’s influencing the therapeutic pipeline. Dr. Taylor, the Bernett Johnson Endowed Professor of Dermatology at the University of Pennsylvania Perelman School of Medicine, outlines current and future treatments, including JAK inhibitors, metformin, and vitamin D.

For more on hair loss, join us on Saturday, June 27, for Hair and Scalp Disorders: The Rx Pad and Beyond, a virtual, one-day conference. The program provides a full-spectrum perspective on hair and scalp management, from diagnosis to therapeutics to nutrition and lifestyle factors. Led by co-chairs Adam Friedman, MD, and Amy McMichael, MD, every session emphasizes practical tools, decision-making, and real-world implementation. Register today!

Genetic Ancestry and Skin Disease: From the SOCU Poster Hall

By Medical Dermatology

genetic ancestry and skin disease

Skin of color dermatology is evolving beyond race-based categories as researchers explore connections between genetic ancestry and skin disease.

Research outlined in a poster presented at Skin of Color Update found that genetically inferred ancestry predicts gene expression differences more accurately than self-identified race, with more than 8% of highly expressed genes—and more than 19% of skin-related genes—showing variation between ancestry groups. These differences, including genes linked to conditions such as lichen planus and skin cancer, may influence disease risk, severity, and treatment response.

In this Next Steps in Derm commentary, poster author Emily Uh, BS, shares the clinical impact of these and other findings about genetic ancestry and skin disease. While genetic ancestry should complement—not replace—clinical evaluation and consideration of social factors, ancestry-informed research may help advance precision dermatology and improve care for diverse populations.

For more articles on skin of color dermatology, including research summaries and video interviews with leading experts, visit the Skin of Color page of Next Steps in Derm.

Vulvar Dermatoses: From the SOCU Poster Hall

By Uncategorized

vulvar dermatoses

Vulvar dermatoses are often underdiagnosed in women with skin of color. Cultural stigma, structural and educational barriers, and gaps in research and clinical training all play a role in limiting care. Patients may self-manage symptoms and only seek care when the disease becomes severe. Once they seek care, they may experience gaps in clinician understanding and recognition of the severity of the disease and its quality of life impacts. These clinical barriers may lead to undertreatment.

A poster presented at Skin of Color Update examined these challenges and highlighted the need for more equitable, culturally informed approaches to vulvar dermatoses. In this Next Steps in Derm commentary, lead author Grace Herrick shares the results of a comprehensive narrative review that identified challenges and barriers to care, including the experience of shame. She also outlines a paradigm shift in how dermatology clinicians should approach vulvar health in populations that have been historically marginalized.

Hidradenitis Suppurativa in Patients with Skin of Color

By Sessions

hidradenitis suppurativa

Hidradenitis suppurativa (HS) is one of the most difficult-to-treat, chronic inflammatory diseases in dermatology, particularly for patients with skin of color. At Skin of Color Update, Tiffany Mayo, MD, led a case-based discussion highlighting earlier recognition, holistic management, and existing and emerging therapies for HS. She emphasized a simple, highly sensitive screening question to reduce diagnostic delays, which currently average 7–10 years, and reviewed the complex immunologic pathogenesis and systemic comorbidities associated with HS.

This session summary outlines practical takeaways, including the importance of reducing patient stigma by reframing misconceptions about causation, while setting realistic expectations — HS is a chronic, noninfectious disease requiring long-term management. Updated U.S. and European guidelines now support a structured, severity-based approach to treatment, incorporating both flare management and maintenance care. Dr. Mayo’s session emphasized holistic, patient-centered care and emerging therapies that can help reduce delays and improve outcomes.